

Oral vs Injectable Hormones: Why the Routes Differ
Updated: 3 days ago
By HGHThailand Team
Oral vs injectable hormones differ mainly because of what happens between the mouth and the bloodstream. A swallowed peptide meets acid, enzymes, the intestinal wall and the liver. An injected compound enters tissue or blood directly and skips those steps. Neither route is inherently better; each has its own considerations.
Key points
A hormone's route of administration decides which barriers it meets before it reaches the bloodstream.
Swallowed peptide and protein hormones face acid, digestive enzymes, a restrictive intestinal wall and the liver; typically under 1% of an oral peptide reaches general circulation (Ali Hussein et al., 2026).
Injected compounds enter tissue or blood directly, so they do not pass through the digestive tract or first-pass metabolism.
Approved medicines and research-grade or unapproved products are different things, and the route alone does not tell you which you have.
Route is a pharmacology topic, not a recommendation about what any person should use.
Oral vs injectable hormones: what the route means
Route of administration is simply the path a compound takes to enter the body: swallowed, injected, absorbed through the skin, or held under the tongue. For hormone products, the route is not a minor detail. Each route presents a different set of physical and chemical obstacles, and those obstacles decide how much of a compound survives long enough to reach the bloodstream. The same molecule can behave very differently depending on how it is delivered.
Why oral peptide and protein hormones are poorly absorbed
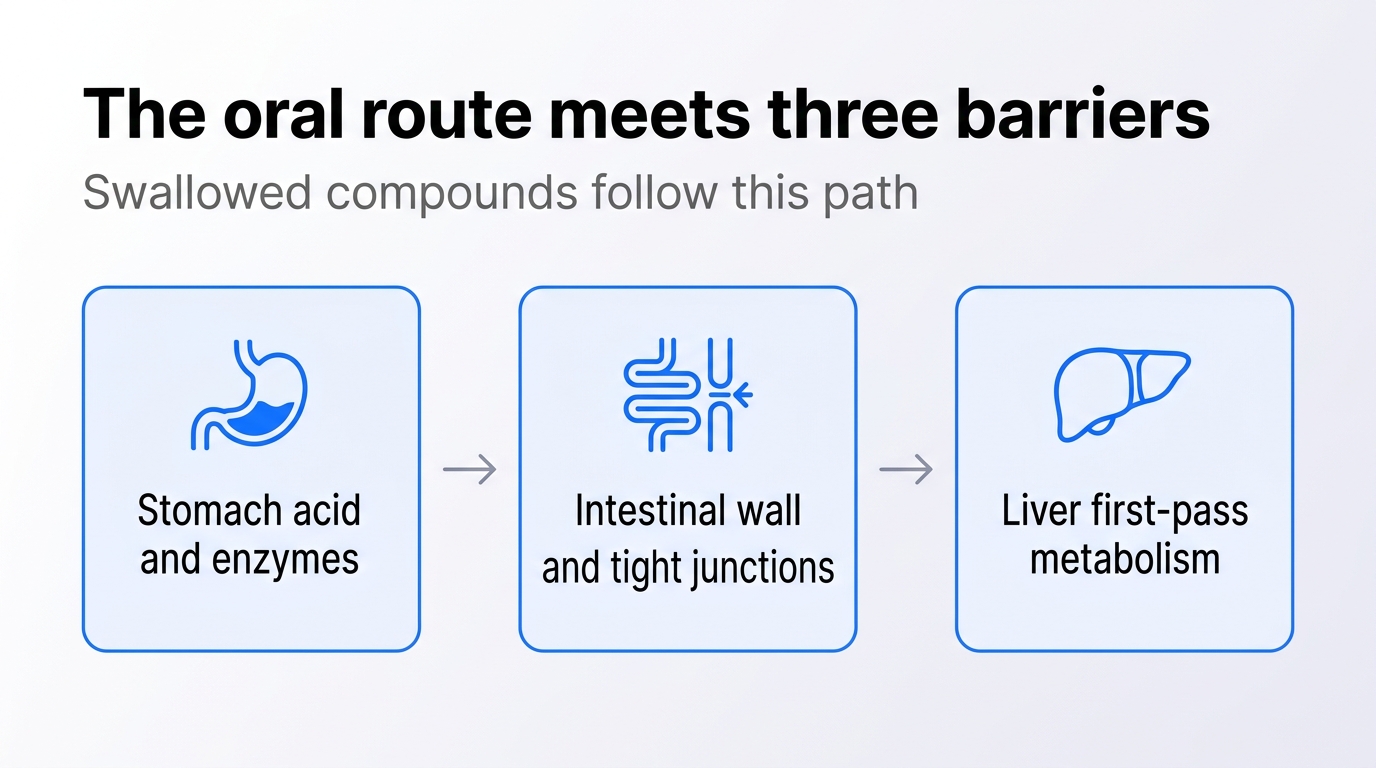
Enzymes in the stomach and gut
The digestive tract is built to break proteins and peptides into smaller pieces so the body can absorb them as nutrients. That same machinery does not distinguish between food protein and a therapeutic peptide. Ali Hussein et al. (2026) note that peptide drugs face proteolytic degradation in the stomach and small intestine, together with a changing pH along the gastrointestinal tract. Stability varies widely: some peptides are broken down within minutes in simulated gastric fluid, while more stable synthetic analogues survive far longer. Degradation reduces how much intact compound remains available for absorption.
The intestinal wall as a size and solubility filter
Even when a peptide survives the gut, it still has to cross the intestinal lining. That lining is a single layer of cells sealed to each other by tight junctions. Ali Hussein et al. (2026) report that these junctions have a pore size of roughly 4 to 8 angstroms, expandable to about 10 to 30 angstroms, giving a molecular weight cutoff for this paracellular route of only slightly above 3 to 5 kilodaltons. The same review explains that the fatty cell membrane makes transcellular permeability of large, hydrophilic molecules difficult. Peptides are typically large and water-loving, so both the paracellular and the transcellular path restrict them.
The result is a hard ceiling on absorption. Ali Hussein et al. (2026) state that less than 1% of orally administered peptide therapeutics typically reaches the systemic circulation.
First-pass metabolism: the liver hurdle
A compound absorbed from the intestine does not enter general circulation immediately. Blood from the gut travels by the portal vein to the liver first. Hepatic first-pass metabolism is one of the barriers Vasović et al. (2026) list for orally administered peptides, alongside acidic pH, proteolytic degradation, mucus and tight junctions. In practical terms, the liver is the body's main site of drug metabolism, so a compound can be chemically modified or cleared there before it is distributed to the rest of the body. That processing is why the amount reaching the bloodstream can differ between a swallowed and an injected route, even for the same molecule.
Why injections do not meet the same barriers
An injected compound does not pass through the mouth, stomach or intestine. It is placed into tissue or blood rather than swallowed, so it does not meet the acid and proteolytic enzymes of the digestive tract and does not cross the intestinal wall on the way to the bloodstream. It also avoids the first-pass metabolism that follows intestinal absorption. This is a difference in route, not a difference in the compound itself.
Vasović et al. (2026) note that the unfavourable properties of peptides, including short residence time and rapid clearance, mean peptide medicines are mostly administered parenterally. Insulin is the example that review uses. An injection does not make a molecule inherently stronger; it simply removes a set of barriers that the swallowed route would impose. Injections also carry their own considerations, such as the need for sterile technique and the risks of any procedure that breaks the skin, which are outside the scope of this article.
Small molecules and peptides are not the same problem
Not all hormone products face the same difficulty. Hormones belong to different molecular classes, and their chemistry shapes what a given route can realistically do. Vasović et al. (2026) describe peptide therapeutics as occupying a position between small organic compounds and large protein biomolecules.
Human growth hormone is a peptide hormone that acts through the growth hormone receptor (Wang et al., 2023), and it is secreted by the pituitary gland under the control of hypothalamic signals and feedback from insulin-like growth factor 1 (Zhang et al., 2026).
The barriers described above are specific to larger, enzyme-sensitive molecules. Small organic compounds are a separate class and behave differently, so findings for one class do not transfer to another.
Property of peptide and protein hormones | What the cited reviews report |
Molecular class | Between small organic compounds and large proteins (Vasović et al., 2026) |
Size and solubility | Relatively large; often highly hydrophilic (Ali Hussein et al., 2026) |
Stability in the gut | Sensitive to proteolytic enzymes; varies between peptides (Ali Hussein et al., 2026) |
Typical oral absorption | Less than 1% of the peptide reaching systemic circulation (Ali Hussein et al., 2026) |
First-pass step | Hepatic first-pass metabolism is one listed barrier (Vasović et al., 2026) |
Usual clinical route | Predominantly parenteral for peptide medicines (Vasović et al., 2026) |
Table note: every entry comes from the two reviews cited; the figures are class-level, not product-specific.
What the research says, and its limits
Most of the physiology above comes from recent peer-reviewed reviews, not from experimental trials of hormone products in people. Reviews summarise many studies and can smooth over differences between compounds. An octapeptide and a full-length protein do not behave the same way in the gut, and structural changes such as cyclisation or lipidation can shift oral absorption between one peptide class and another (Ali Hussein et al., 2026). The often-cited figure that under 1% of an oral peptide reaches circulation is a class-level statement about peptides in general, not a value measured for any specific product (Ali Hussein et al., 2026).
Oral delivery is also an active research area. Vasović et al. (2026) survey bioinspired systems and device-assisted approaches that aim to improve oral peptide absorption; these are experimental directions, and they do not change the current class-level picture.
Nothing here establishes what any product does in any person. Absorption depends on the exact molecule, its formulation and the individual.
Approved medicines and research-grade products
An approved medicine and a research-grade or unapproved product are not the same thing, even when the compound name looks similar. An approved medicine has been assessed by a regulator for a specific use, with a defined formulation and quality control. Research-grade material is sold for laboratory work and is not intended for human use. A product's route of administration says nothing about which category it falls into, and this article takes no position on any particular product.
Regulation and context
Rules on how hormone products may be sold, and whether a prescription is needed, differ by country and by compound, and they change over time. Because this varies, a reader who wants to understand the position of a specific product should check the rules that apply where they live, with their national medicines regulator. This article makes no claim about the legal or regulatory status of any product in any market.
FAQ
Why can most peptide hormones not be taken as a pill?
Because the digestive tract breaks proteins and peptides down, and the intestinal wall restricts large, water-loving molecules. Typically less than 1% of an oral peptide reaches general circulation, and the liver further processes much of what is absorbed (Ali Hussein et al., 2026; Vasović et al., 2026).
What is first-pass metabolism?
It is the processing a compound undergoes after it is absorbed from the intestine and carried to the liver by the portal vein, before it reaches the rest of the body. For oral peptides this hepatic first-pass step is one of several barriers that reduce how much active compound circulates (Vasović et al., 2026).
Are oral and injectable forms of the same hormone interchangeable?
No. Even for the same molecule, the two routes meet different barriers, so the amount that reaches the bloodstream can differ substantially, which is why peptide medicines are predominantly given by injection. This is a difference in route, not a statement that any injected product is safe or suitable (Vasović et al., 2026).
Does molecular size decide the route?
It is one major factor. Peptides and proteins are larger, often hydrophilic and sensitive to enzymes, while small organic compounds are chemically more varied. Size, solubility, stability and the first-pass step together shape what a route can deliver (Ali Hussein et al., 2026; Vasović et al., 2026).
*This article is informational only and is not medical advice. It does not recommend any product or route. Consult a qualified healthcare professional for personal guidance.*
Sources
Ali Hussein L, Nedic A, Sitovs A, Mohylyuk V. Natural Oral Absorption of Therapeutic Peptides: Mechanisms and Physiological Determinants. Pharmaceutics. 2026;18(9):1091. PMID 42797266. DOI 10.3390/pharmaceutics18091091. https://doi.org/10.3390/pharmaceutics18091091
Vasović S, Vasović L, Martić N, Chirasatitsin S, Vasović V, Vukmirović S, Pavlović N. Emerging Technologies for Oral Peptide Delivery: From Bioinspired Systems to Smart Device-Assisted Drug Delivery. Pharmaceuticals (Basel). 2026;19(9):1328. PMID 42797374. DOI 10.3390/ph19091328. https://doi.org/10.3390/ph19091328
Zhang Q, Ma Y, Liu Y, Ali A, Wang Y, Zhang F, Chen L, Zhan X. Proteoformics-driven new concept of human growth hormone in clinical endocrinology. Frontiers in Endocrinology. 2026;17:1842422. PMID 42694310. DOI 10.3389/fendo.2026.1842422. https://doi.org/10.3389/fendo.2026.1842422
Wang Y, Kim M, Buckley C, Maynard HD, Langley RJ, Perry JK. Growth hormone receptor agonists and antagonists: From protein expression and purification to long-acting formulations. Protein Science. 2023. PMID 37428391. DOI 10.1002/pro.4727. https://doi.org/10.1002/pro.4727