

HGH vs IGF-1: Key Differences, Functions, and Regulation
Updated: 3 days ago
By HGHThailand Team
HGH and IGF-1 are two different hormones that work as one system. A core difference between HGH and IGF-1 is where each is produced: HGH in the pituitary gland, IGF-1 mainly in the liver. HGH is released in pulses, while IGF-1 is made in response to HGH and stays in the blood longer. HGH acts directly on tissues and indirectly through IGF-1.
Key points
HGH comes from the pituitary gland; IGF-1 is produced mainly in the liver.
HGH is released in pulses, while most IGF-1 travels bound to carrier proteins that extend its time in the blood.
HGH drives IGF-1 production; IGF-1 then feeds back to reduce HGH release.
The two hormones overlap in growth and metabolism, but they are regulated and measured differently.
Neither hormone is approved for anti-aging, bodybuilding or athletic enhancement.
HGH vs IGF-1: What Are They? (Growth Hormone vs IGF-1)
HGH (human growth hormone, also called somatotropin) is a protein hormone made of 191 amino acids. It is expressed in the somatotropic cells of the pituitary gland. IGF-1 (insulin-like growth factor 1) is a separate peptide hormone, produced mainly in the liver, that carries out many of the growth and metabolic effects attributed to HGH.
The two names can be confusing because both hormones are described together as one system, the "GH/IGF-1 axis." This axis is why growth hormone vs IGF-1 is usually discussed as one topic rather than two. They are not the same molecule and they are not the same medicine. HGH is a pituitary hormone; IGF-1 is its main downstream mediator.
Where each hormone is made and how it travels
The two hormones differ in where they start and how they move through the body.
HGH is secreted by the pituitary gland under the control of the hypothalamus. Its secretion is episodic and pulsatile: levels rise in peaks and fall to very low levels between them. That pattern is one reason a single random HGH measurement is hard to interpret, a point clinicians take into account when testing the axis.
IGF-1 produced in the liver is the major contributor to the circulating pool; the liver is its main source. In the blood, roughly 99% of IGF-1 is bound with high affinity to six IGF-binding proteins (IGFBP-1 to -6) and to the acid-labile subunit (ALS); less than 1% circulates free. Because it is carried by these proteins, IGF-1 has a much longer half-life than HGH and its blood level is far more stable. The binding proteins also control how much IGF-1 reaches tissues.
Feature | HGH (somatropin) | IGF-1 (mecasermin) |
Main source | Anterior pituitary gland | Mainly the liver |
Release pattern | Pulsatile, with peaks and troughs | Largely continuous and protein-bound |
Time in the blood | Short; cleared quickly | Extended by IGFBP/ALS binding |
Main actions | Growth signalling; fat, protein and glucose metabolism | Mediates bone growth and anabolic effects; local tissue actions |
Regulatory status (US, verified) | Prescription biologic, approved for a limited set of conditions | Prescription medicine, approved for a narrow pediatric use |
How HGH and IGF-1 are linked
The body's own growth hormone is the main regulator of IGF-1 production in healthy states. HGH stimulates IGF-1 synthesis and secretion, and IGF-1 then inhibits growth hormone secretion through a negative feedback loop: when IGF-1 rises, HGH release tends to fall. This self-regulating cycle is known as the growth hormone feedback loop.
At the level of the brain, growth hormone release is controlled by two opposing hypothalamic signals. Growth hormone-releasing hormone (GHRH) stimulates it, while somatostatin inhibits it. IGF-1 feeds into this control: it reduces GHRH and increases somatostatin, which together lower pituitary HGH output.
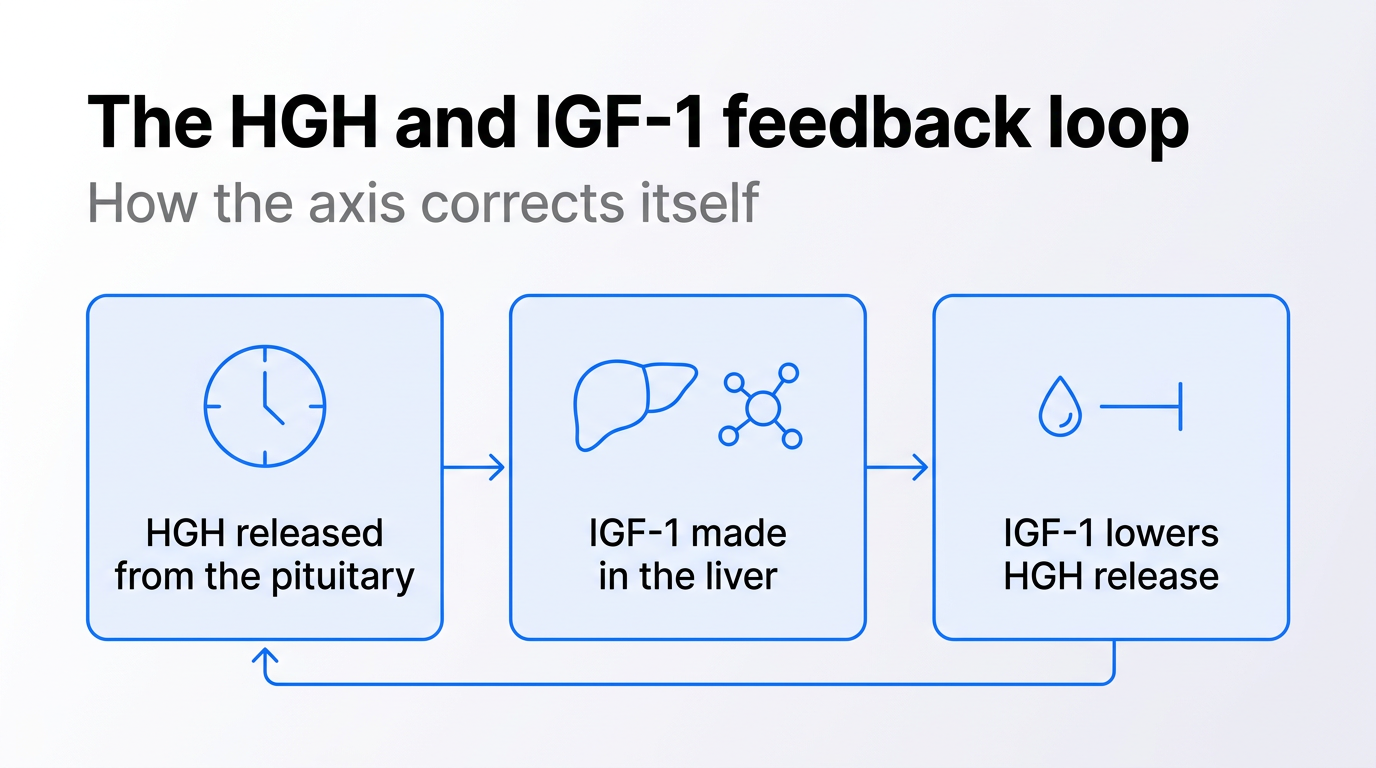
The relationship is not purely mechanical. Research also shows that nutrition and insulin reaching the liver help set how sensitive the liver is to growth hormone, and therefore how much IGF-1 is produced. In states such as fasting, chronic liver disease or diabetes, GH and IGF-1 levels can move in ways that do not follow the simple one-way link, which is why the axis is read as a whole rather than from a single number.
What each hormone does
In children, the GH/IGF-1 axis is central to linear growth. In adults, its role is mainly metabolic.
HGH acts directly in several tissues. It increases lipolysis and lipid oxidation, stimulates protein synthesis (including in skeletal muscle), opposes insulin action in a way that can raise glucose, and influences how the kidneys handle phosphate, water and sodium.
IGF-1 mediates bone growth and anabolic metabolism and also acts locally in tissues. Its effects overlap with HGH, which is why the two are often discussed together, but overlapping effects do not make them interchangeable.
What research says about aging and off-label use
HGH and IGF-1 have drawn attention as possible "anti-aging" therapies because their levels change with age and they influence body composition. That interest should not be confused with evidence that they are safe or effective for healthy aging.
A 2025 clinical review in *Frontiers in Aging* concludes that the long-term safety and efficacy of these therapies for promoting healthy aging remain uncertain, and that findings are mixed. This is a research question, not an approved use.
The US Food and Drug Administration (FDA) states that HGH has important benefits but also serious known risks, and that it is not approved for anti-aging, bodybuilding or athletic enhancement. Reported risks include a possible increased risk of cancer, nerve pain, and elevated cholesterol and glucose levels. Under US law, distributing or possessing HGH with intent to distribute it for those unapproved uses is prohibited.
How HGH and IGF-1 are regulated
Regulatory status can differ by country. The statements below are for the United States and were checked against primary sources.
Somatropin (recombinant human growth hormone) is a prescription biologic. It is approved for a limited set of conditions, including certain types of growth failure and short stature in children, and growth hormone deficiency in adults (as well as short bowel syndrome in patients on specialized nutritional support).
Mecasermin (recombinant IGF-1) is a prescription medicine approved for a narrow pediatric use: growth failure in children with severe primary IGF-1 deficiency, or with growth hormone gene deletion who have developed neutralizing antibodies to growth hormone.
When comparing somatropin vs mecasermin, the two prescription biologics have distinct indications. Somatropin, one of the recombinant human growth hormone formulations, belongs to the wider growth hormone category. Both are prescription medicines used only under medical supervision for diagnosed conditions, and both carry known risks. The approvals described above are the only approved uses; the FDA's anti-aging and bodybuilding warning above still applies. This article describes what the research and regulators report; it does not suggest any use.
FAQ
Are HGH and IGF-1 the same thing?
No. HGH is a pituitary hormone; IGF-1 is a separate hormone produced mainly in the liver in response to HGH. They are linked as one axis but are different molecules with different patterns in the blood.
Does HGH turn into IGF-1?
HGH does not become IGF-1. It stimulates the liver (and other tissues) to produce IGF-1, which then mediates many of HGH's growth effects.
Which one lasts longer in the blood?
IGF-1. Because most IGF-1 is bound to carrier proteins, it has a much longer half-life and a more stable blood level than HGH, which is cleared quickly between pulses.
Are HGH or IGF-1 approved for anti-aging or bodybuilding?
No. In the United States, the FDA states that HGH is not approved for anti-aging, bodybuilding or athletic enhancement, and IGF-1 has a narrow pediatric approval. Neither is approved for those purposes.
Why do doctors measure both?
Because they give different information. HGH is pulsatile and hard to interpret from a single sample, while IGF-1 is more stable, so the two are usually read together when the axis is evaluated.
Disclaimer
This article is provided for general information only and is not medical advice. It describes what published research and regulators report; it is not a recommendation to use any product, and it does not replace advice from a qualified healthcare professional. If you have questions about growth hormone, IGF-1 or your own health, speak with a doctor or pharmacist.
Sources
Yuen KCJ, Hjortebjerg R, Ganeshalingam AA, Clemmons DR, Frystyk J. "Growth hormone/insulin-like growth factor I axis in health and disease states: an update on the role of intra-portal insulin." *Frontiers in Endocrinology*, 2024. https://doi.org/10.3389/fendo.2024.1456195
Fernández-Garza LE, Guillen-Silva F, Sotelo-Ibarra MA, Domínguez-Mendoza AE, Barrera-Barrera SA, Barrera-Saldaña HA. "Growth hormone and aging: a clinical review." *Frontiers in Aging*, 2025. https://doi.org/10.3389/fragi.2025.1549453
US Food and Drug Administration. "Import Alert 66-71: Detention Without Physical Examination of Unapproved Human Growth Hormone (HGH)." Published 04/07/2026. https://www.accessdata.fda.gov/cms_ia/importalert_204.html
DailyMed (US National Library of Medicine). "INCRELEX (mecasermin) injection: Highlights of Prescribing Information." https://dailymed.nlm.nih.gov/dailymed/lookup.cfm?setid=d5b2b0e1-c523-468d-9a0b-4ae4e4a8dbce