

Growth Hormone and Aging: How Natural Release Changes
Updated: 3 days ago
By HGHThailand Team
Growth hormone is released by the pituitary in pulses, with the largest pulse arriving during deep sleep. The link between growth hormone and aging is a gradual decline in output, a shift called the somatopause. Studies of sleep, exercise and diet describe how these factors relate to natural release; they do not identify a lifestyle habit that restores young adult levels.
Key points
Growth hormone is secreted by the pituitary in pulses, controlled by two opposing hypothalamic signals, GHRH which stimulates release and somatostatin which inhibits it (Kasprzak, 2026).
The largest pulses arrive during deep, slow-wave sleep, when somatostatin withdrawal combines with GHRH release (Veldhuis and Iranmanesh, 1996).
Output declines with age in a pattern called the somatopause. One review of the literature puts the average at about 14 percent per decade from around age 30 (Kasprzak, 2026).
High-intensity exercise produces a marked pulsatile rise in growth hormone, and a 12-week combined training program was linked with higher levels (Ferrante et al., 2026).
Body composition, especially visceral fat, is a strong negative determinant of growth hormone output. In one review, adiposity attenuated or abolished the links between GH and age, testosterone and sleep (Veldhuis and Iranmanesh, 1996).
How growth hormone is released in the body
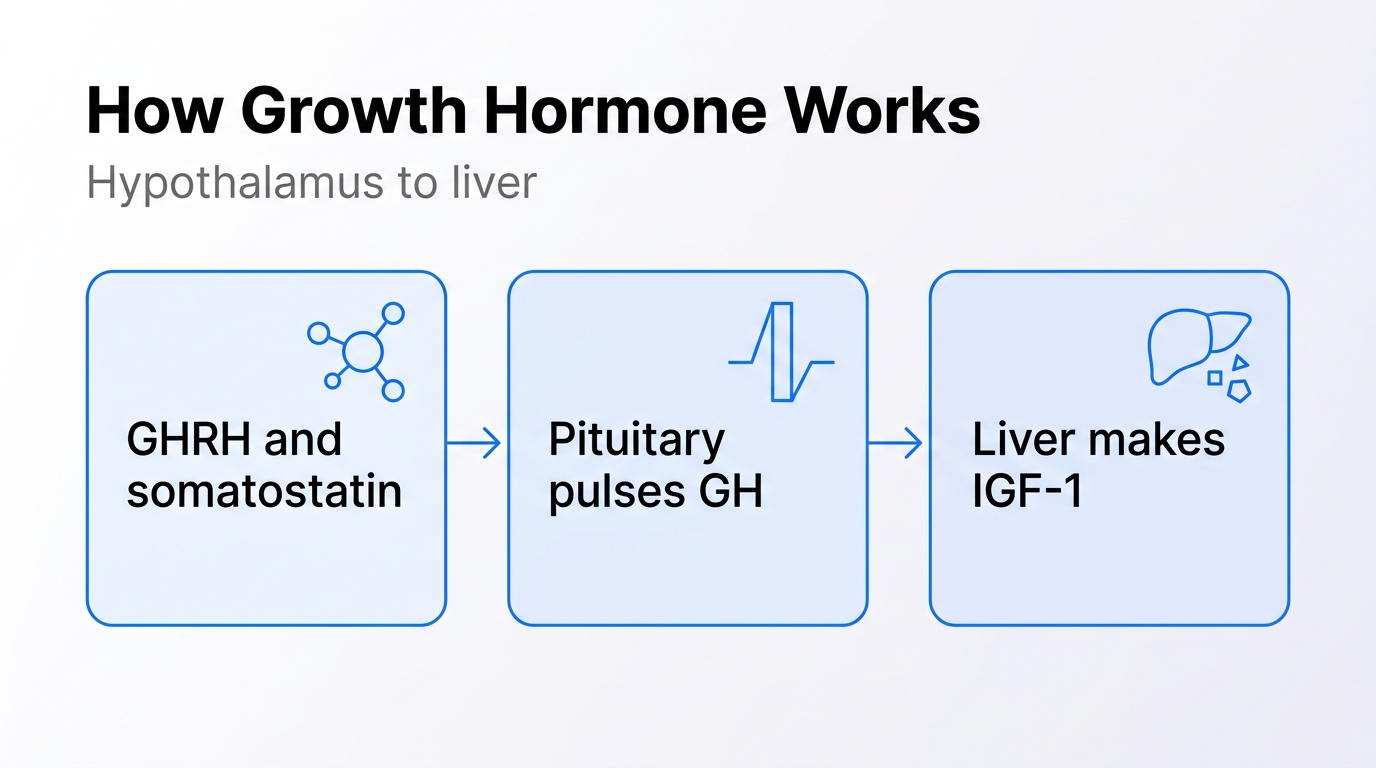
Growth hormone (GH), also called somatotropin, is made by cells called somatotrophs in the anterior lobe of the pituitary gland. These cells release the hormone in pulses rather than at a steady rate, so blood levels rise and fall through the day (Kasprzak, 2026).
Two hypothalamic peptides set the pattern. Growth hormone releasing hormone (GHRH) stimulates release, while somatostatin inhibits it. The balance between them shapes the size and timing of each pulse (Kasprzak, 2026). The main target of GH is the liver, which responds by producing insulin-like growth factor 1 (IGF-1). IGF-1 carries many of the growth-promoting effects of GH on bone, muscle and other tissues, and it also feeds back to the hypothalamus and pituitary to keep the system in check (Kasprzak, 2026).
Because release is pulsatile, a single random blood measurement captures only one moment in that cycle.
Growth hormone and aging: why output declines
The hypothalamic-pituitary-somatotropic axis is one of the endocrine systems that decline with age (Kasprzak, 2026). The term somatopause describes the age-related fall in pulsatile GH levels and the resulting drop in blood IGF-1 (Kasprzak, 2026).
The timing is gradual. In one review, the decline in GH secretion in humans begins at around age 30, is greatest around age 70, and averages about 14 percent per decade (Kasprzak, 2026). That figure is an estimate drawn from a review of the literature rather than a single primary measurement study. Other modelling has described a steeper, exponential fall, which shows that estimates vary between studies and between individuals (Veldhuis and Iranmanesh, 1996).
The cause is still debated. Some work points to reduced GHRH signalling, and some to increased somatostatin tone. In men, one line of evidence suggests the main driver is atrophy of the pituitary somatotrophs secondary to lower endogenous GHRH, rather than a rise in somatostatin (Kasprzak, 2026).
The same review records that higher GH and IGF-1 levels are associated with several cancers, including breast, prostate and colorectal cancer, and that lifelong GH and IGF-1 deficiency has been linked with longer lifespan in animal models (Kasprzak, 2026).
Sleep and natural growth hormone release
Sleep is one of the strongest natural influences on GH. In a review of the GH and IGF-1 axis, deep sleep in stages 3 and 4 was accompanied by markedly increased pulsatile GH secretion, which the authors explained by somatostatin withdrawal combined with hypothalamic GHRH release (Veldhuis and Iranmanesh, 1996).
That finding places the biggest daily GH pulse inside deep, slow-wave sleep for many people. The same review found that the relationship between GH and sleep weakens or disappears as body weight and visceral fat increase, so sleep is not the only factor (Veldhuis and Iranmanesh, 1996). Much of this sleep and body-composition work dates from the 1990s, so the reported effect sizes are historical estimates.
None of this shows that adding hours of sleep will restore young adult levels. It shows that deep sleep is the natural setting in which a large share of nightly GH release occurs.
Exercise and growth hormone
Exercise is another studied stimulus. A 2026 study of combined aerobic and resistance training describes GH as showing a marked pulsatile increase during high-intensity exercise, with lipolytic and anabolic effects mediated in part by IGF-1 (Ferrante et al., 2026).
The same paper notes that resistance and high-intensity exercise affect testosterone and GH secretion differently, and that the response depends on age, biological sex, nutritional status, nutrient timing and training status (Ferrante et al., 2026). In its 12-week trial, 60 adults were randomly allocated to an exercise group of 30 or a control group of 30, and the exercise group showed increased GH levels alongside lower fasting insulin, cortisol, glucose and HOMA-IR (Ferrante et al., 2026).
These are acute responses and short-term training effects in a 12-week study of 60 adults, not evidence that exercise reverses the somatopause. The authors describe combined exercise as a way to support endocrine and metabolic health (Ferrante et al., 2026).
Diet, fasting and growth hormone
Nutrition interacts with the axis in several ways. GH secretion is inhibited by IGF-1 feedback and by other signals including somatostatin and insulin (Kasprzak, 2026). Glucose stimulates somatostatin release, which in turn restrains GH (Kasprzak, 2026). Amino acids, by contrast, stimulate pituitary hormone secretion, and a randomized crossover study in 15 healthy adults found that somatostatin signalling constrains the GH response to an amino acid infusion (Sturlaugsson Jóhönnuson et al., 2026). That study measured the acute response to an amino acid infusion and did not test aging, so it informs the mechanism rather than the age-related decline.
Fasting is often mentioned in this context, but the direction of the effect needs care. A review of intermittent and periodic fasting describes the suppression of the mTOR and IGF-1 axis as one of the core responses to fasting, alongside activation of AMPK and sirtuins (Liu and Guo, 2026). On this evidence, fasting is associated with lower IGF-1 signalling rather than higher.
Body composition may matter more than any single food. In the GH and IGF-1 review, obesity was a strong negative determinant of GH production, with an estimated 50 percent decrease in daily GH secretion for each 1.5 kg/m2 increase in body mass index, and the links between GH and age, testosterone or sleep were attenuated or abolished by adiposity (Veldhuis and Iranmanesh, 1996).
What the evidence says about raising growth hormone
The natural question after reading this is whether GH can be raised, and whether that helps. The evidence on treating the somatopause is limited. A 2026 review of the topic reports that GH replacement for the somatopause produces only minor changes in body composition, with no clinically significant improvements in health or well-being, and that numerous adverse side effects have been documented (Hoffman and Gangotena, 2026).
The same review notes that most endocrinologists agree GH therapy for the somatopause cannot be recommended unless new, carefully performed long-term studies show otherwise (Hoffman and Gangotena, 2026).
This article does not cover how GH is used as a medicine, and nothing here is a recommendation. Any decision about testing or treatment belongs to a qualified clinician who can weigh the risks for an individual.
FAQ
Does growth hormone decline with age?
Yes. The age-related fall in pulsatile GH and blood IGF-1 is called the somatopause. One review puts the average decline at about 14 percent per decade from around age 30, greatest near age 70, though estimates vary between studies (Kasprzak, 2026; Veldhuis and Iranmanesh, 1996).
When is growth hormone released?
In pulses rather than steadily, with the largest pulses during deep, slow-wave sleep, when somatostatin withdrawal combines with GHRH release (Veldhuis and Iranmanesh, 1996).
Does exercise increase growth hormone?
High-intensity exercise produces a marked pulsatile rise in GH, and a 12-week combined aerobic and resistance program was associated with higher GH levels in 60 adults (Ferrante et al., 2026). This is an acute response and a training effect, not a treatment for the somatopause.
What does fasting do to the GH and IGF-1 axis?
Reviews link intermittent and periodic fasting with suppression of the mTOR and IGF-1 axis, so the evidence points to lower IGF-1 signalling rather than higher (Liu and Guo, 2026). Body composition, especially visceral fat, is a stronger determinant of GH output (Veldhuis and Iranmanesh, 1996).
Is growth hormone therapy recommended for aging?
A 2026 review reports only minor body-composition changes, no clinically significant benefit to health or well-being, and documented adverse effects from GH replacement for the somatopause, so it is not recommended (Hoffman and Gangotena, 2026).
Disclaimer
This article is for information only and is not medical advice. It does not cover dosing, therapy or how to use any medicine. Consult a qualified healthcare professional about diagnosis, testing and treatment.
Sources
Kasprzak A. Somatostatin in Aging: Correlations with Selected Central Nervous System and Gastrointestinal Tract Diseases. Int J Mol Sci. 2026. PMID 42196227. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC13207217/
Veldhuis JD, Iranmanesh A. Physiological regulation of the human growth hormone (GH)-insulin-like growth factor type I (IGF-I) axis: predominant impact of age, obesity, gonadal function, and sleep. Sleep. 1996;19(Suppl 10):S221-S224. PMID 9085516. https://pubmed.ncbi.nlm.nih.gov/9085516/
Hoffman AR, Gangotena AM. Treatment of the somatopause: A perennial question. Growth Horm IGF Res. 2026. PMID 42308660. https://pubmed.ncbi.nlm.nih.gov/42308660/
Ferrante L, Latino F, Amato G, Tafuri MG. Combined Aerobic and Resistance Exercise Program in Adults: Endocrine and Metabolic Adaptations. Life (Basel). 2026. PMID 42653053. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC13514691/
Liu Y, Guo H. Intermittent and periodic fasting: molecular mechanisms, health benefits and research challenges. Front Nutr. 2026. PMID 42812993. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC13621515/
Sturlaugsson Jóhönnuson EM, Reiche J, Richter MM, Wewer Albrechtsen NJ. Differential somatostatin sensitivity of corticotropic and somatotropic responses following amino acid infusion. Endocr Connect. 2026. PMID 42696271. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC13641144/